
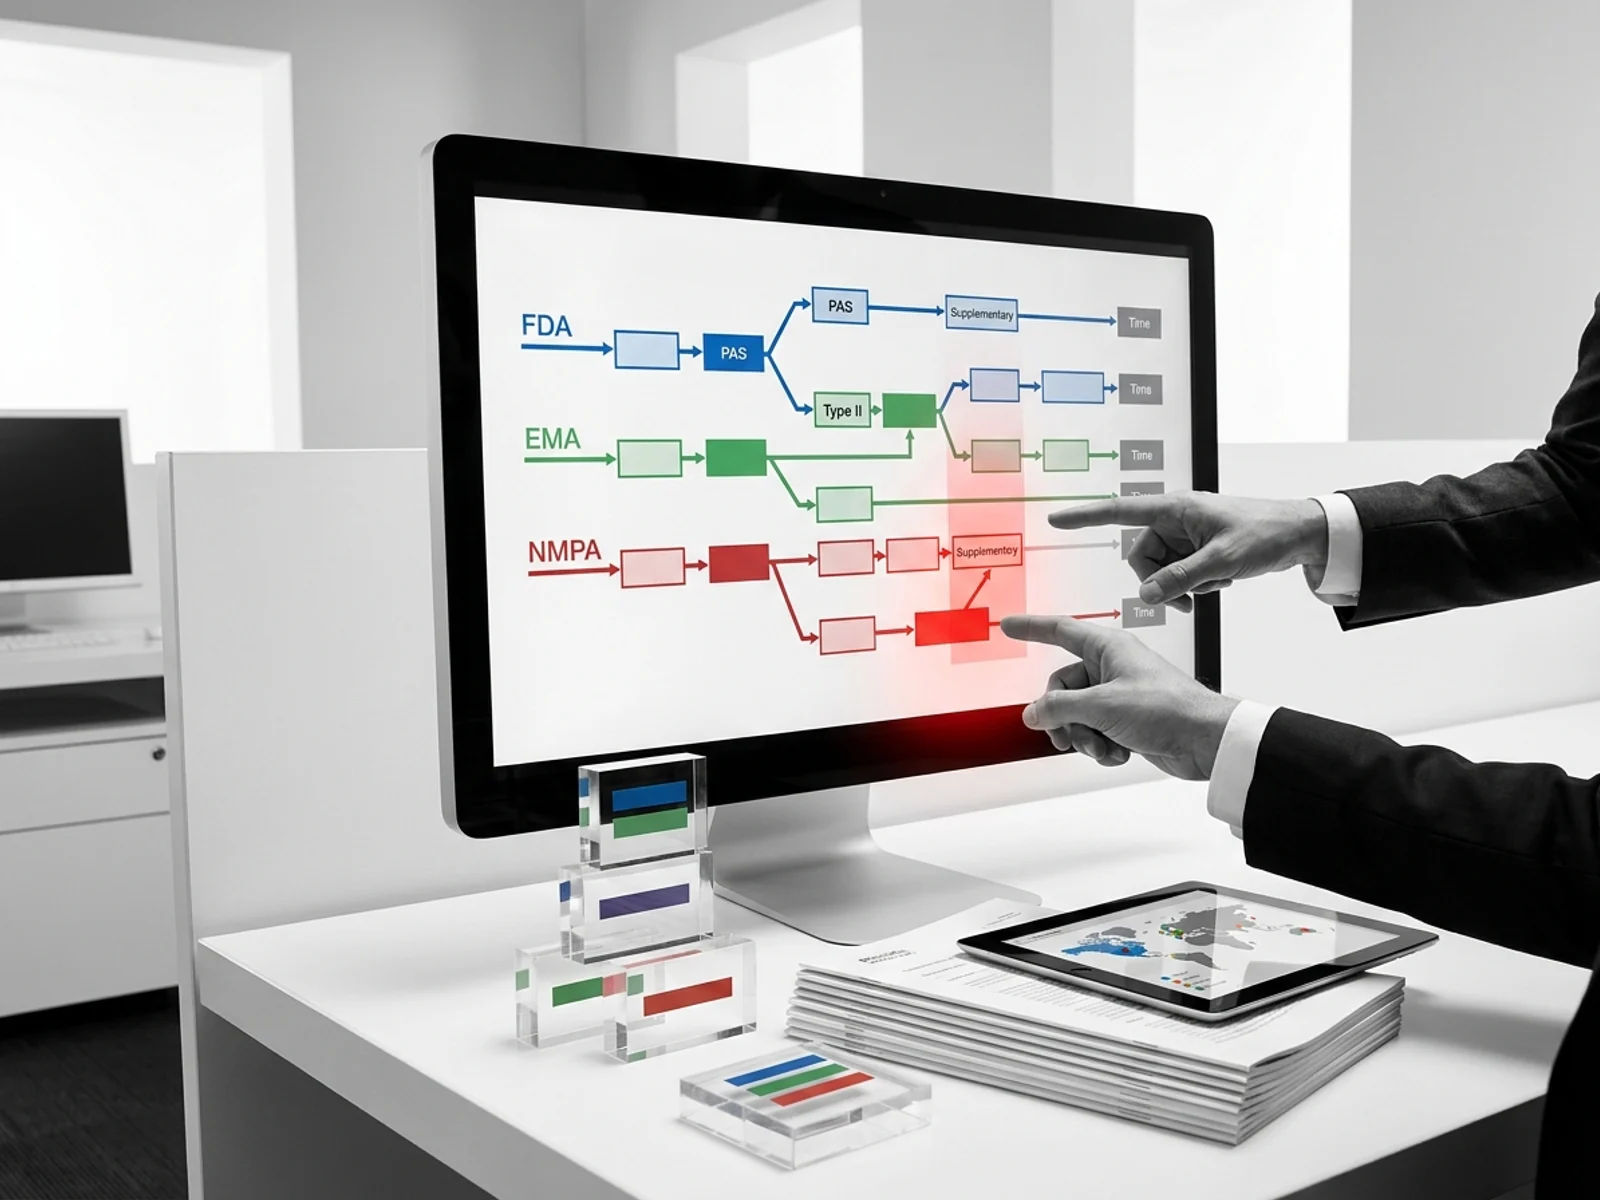
A biologic manufacturer wants to transfer a drug product fill-finish step from Site A to Site B. In the US, this change requires a Prior Approval Supplement (PAS) under 21 CFR 601.12. In the EU, the same change is a Type II variation under Regulation (EC) No 1234/2008. In China, the NMPA requires a separate supplementary application. In Brazil, ANVISA may classify it differently. The data packages overlap but are not identical, and the timelines diverge by months.
This is the core problem of global CMC change classification mismatch: the same manufacturing change triggers different regulatory pathways, data requirements, and review timelines across markets. For a product sold in 30+ countries, a single site change can generate dozens of parallel filings, each with its own classification and clock.
This article is for CMC regulatory affairs leads, quality directors, and global regulatory strategists who plan and execute post-approval manufacturing changes across markets.
The three major classification frameworks
FDA (United States): PAS, CBE-30, CBE-0, and Annual Report
Under 21 CFR 314.70 (drugs) and 21 CFR 601.12 (biologics), FDA classifies post-approval CMC changes into three tiers based on the potential for adverse effect on product quality:
| Reporting category | Risk level | Timing | Examples |
|---|---|---|---|
| Prior Approval Supplement (PAS) | Major — substantial potential adverse effect | Must be approved before distribution of product made using the change | New manufacturing site, new container closure, change in cell line |
| Changes Being Effected (CBE-30 or CBE-0) | Moderate — moderate potential adverse effect | Distribute 30 days after FDA receipt (CBE-30) or immediately upon submission (CBE-0) | Process parameter changes within validated ranges, new analytical method |
| Annual Report (AR) | Minor — minimal potential adverse effect | Include in the next annual report | Tightening a specification, minor equipment change within design space |
FDA's guidance "Established Conditions: Reportable CMC Changes for Approved Drug and Biologic Products" and ICH Q12 provide the framework for identifying which CMC elements are established conditions (ECs) that require reporting and which are supportive information manageable under the pharmaceutical quality system (PQS).
EMA (European Union): Type IA, Type IB, and Type II
Under EU Regulation (EC) No 1234/2008 and the updated Variation Guidelines effective January 15, 2026, post-approval changes in the EU are classified as:
| Variation type | Risk level | Procedure | Timeline |
|---|---|---|---|
| Type IA (minor) | Minimal impact | Do-and-tell: implement, then notify | ~30 days for acknowledgment |
| Type IB (moderate) | Moderate impact | Tell-and-wait: notify, then implement after assessment | ~30 days for assessment |
| Type II (major) | Significant impact | Prior approval required | 60–90 days assessment, can extend |
Key difference from FDA: In the EU, the variation classification is prescribed in detailed annexes that specify exactly which changes fall into which category, with conditions. If a condition is not met, the change defaults to a higher category (e.g., a Type IA becomes a Type IB).
Non-ICH and emerging markets
Markets outside the ICH cluster (China, India, Brazil, South Korea, Saudi Arabia, etc.) have their own classification systems that are partially aligned with WHO guidelines but diverge in practice:
| Market | Authority | Classification | Key difference from FDA/EMA |
|---|---|---|---|
| China | NMPA/CDE | Supplementary applications; major, moderate, minor categories aligned to ICH Q12 | NMPA adopted ICH Q12 principles in 2023–2024 but implementation guidance (e.g., PACMP) is still evolving. October 2025 draft guidance on post-approval CMC change management for chemical drugs is pending finalization. |
| India | CDSCO | Major/minor variations under Schedule D-II | Timelines and data requirements often less predictable; CDSCO may require full validation data for changes that FDA would accept under CBE-30 |
| Brazil | ANVISA | Post-approval change notifications classified by risk | ANVISA classifies changes into categories I–IV; data requirements are similar to EMA but review timelines are longer (120–180 days for major changes) |
| South Korea | MFDS | Variation applications with prior approval or notification | Aligned partially with ICH; MFDS has adopted some ICH Q8–Q11 principles but Q12 implementation is not yet formalized |
| Saudi Arabia | SFDA | Variation types aligned with EU framework | SFDA often follows EU classification but may request additional stability data |
Where classification mismatches occur
Based on IFPMA's 2025 comparative analysis of global regulatory frameworks for post-approval changes in biotherapeutic products, the following change types are most likely to be classified differently across markets:
1. Analytical method changes
| Change | FDA | EMA | Typical non-ICH |
|---|---|---|---|
| New analytical method for release testing | CBE-30 or CBE-0 | Type IB for chemical methods; Type II for biological/immunological methods | Often requires prior approval with full validation data |
| Tightening specification limits | Annual Report | Type IA | May require notification or prior approval |
| Widening specification limits | PAS or CBE-30 depending on impact | Type II if significant impact; Type IB otherwise | Generally requires prior approval |
The EMA distinguishes between chemical and biological/immunological analytical methods in its classification, which FDA does not. A change in a potency assay for a biologic that is a Type II variation in the EU may be a CBE-30 in the US.
2. Manufacturing site changes
| Change | FDA | EMA | Typical non-ICH |
|---|---|---|---|
| New manufacturing site (drug substance) | PAS | Type II | Prior approval required; may require local batch release |
| Transfer of process within same site | CBE-30 or AR | Type IA or Type IB | Varies; some markets require notification only |
| New contract manufacturing organization | PAS | Type II | Prior approval with full validation and, in some markets, local GMP inspection |
Site changes are the highest-impact category for classification mismatch. In the US, FDA may conduct a Pre-Approval Inspection (PAI) before approving a PAS for a new site. In the EU, the Type II variation timeline is 60–90 days but the rapporteur may request an inspection. In China, NMPA requires its own inspection process with separate timelines.
3. Scale changes
| Change | FDA | EMA | Typical non-ICH |
|---|---|---|---|
| Scale-up of bioreactor within validated range | AR or CBE-30 | Type IA if within approved range | May require prior approval with process validation data |
| Scale-up beyond validated range | PAS | Type II | Prior approval required |
4. Container closure changes
| Change | FDA | EMA | Typical non-ICH |
|---|---|---|---|
| Change to primary container closure | PAS | Type II | Prior approval; some markets require stability data beyond EMA expectations |
| Change to secondary packaging | AR | Type IA | Notification or AR |
5. Process parameter changes
ICH Q12's concept of established conditions (ECs) versus supportive information creates a framework for risk-based reporting. However, not all markets have adopted this framework. Where FDA may accept that a process parameter change falls within the design space and is manageable under the PQS (Annual Report), EMA may require a Type IB variation, and non-ICH markets may require a prior-approval supplement.
ICH Q12 as the alignment framework (and its limits)
ICH Q12, finalized in November 2019, provides the most advanced framework for harmonizing post-approval CMC change management. Its core concepts:
Established Conditions (ECs)
ECs are the CMC elements in a regulatory submission that, if changed, require a regulatory communication to the authority. Everything else is "supportive information" that can be managed under the company's PQS without regulatory notification.
FDA adopted ICH Q12 through its guidance on Established Conditions and Comparability Protocols. FDA's implementation includes:
An Established Conditions Coordinating Committee (ECCC) within the Office of Pharmaceutical Quality
A Q12 Assessment Implementation Team (Q12AIT) for scientific consistency
A Product Lifecycle Management (PLCM) document that lists ECs, reporting categories, and PACMPs in a central repository
As of September 2023, FDA had received 39 applications proposing ECs (6 NDAs, 19 ANDAs, and 14 BLAs), with 28 approved, according to the agency's public data.
EMA implementation has been slower. The EU variation regulation (EC No 1234/2008) does not allow indefinite waiver of reporting. Even under ICH Q12, changes that are classified as supportive information in the US may still require at least a Type IA notification in the EU.
Post-Approval Change Management Protocols (PACMPs)
PACMPs (called Comparability Protocols in the FDA system) allow a sponsor to pre-agree with the regulator on the tests, acceptance criteria, and reporting category for a future change. If the change is executed within the PACMP, the reporting category can be reduced (e.g., from PAS to CBE-30).
China's NMPA issued draft guidance in October 2025 on PACMP-style change management for chemical drugs, signaling alignment with ICH Q12. But this has not yet been finalized for biologics.
Where Q12 alignment breaks down
The IFPMA 2025 analysis identifies several structural barriers:
Regulatory frameworks predate Q12. Most national variation regulations were written before ICH Q12 was finalized. Rewriting these regulations takes years.
Biologics face stricter classification. Under the current EU variation guidelines, several categories of changes for biological products are precluded from the Type IA route, forcing sponsors into Type IB or Type II even when the change is minor. EFPIA has advocated for alignment between biologics and small molecules.
Non-ICH markets may not recognize ECs or PACMPs. A change managed under a PACMP in the US may still require a full supplementary application in China, India, or Brazil, with no credit for the pre-agreed protocol.
Timelines diverge. A PAS in the US takes 4 months (priority, no inspection) to 10 months (standard, with inspection), with 6 months being typical for standard review without inspection. A Type II variation in the EU takes 60–90 days. A supplementary application in China can take 60–200 days depending on complexity. A major change in Brazil can take 120–180 days. These timelines do not align, which means a global change cannot be executed simultaneously.
Operational framework for managing global CMC changes
1. Build a change classification matrix
For each planned CMC change, create a matrix that maps the classification, data requirements, and timeline for every market where the product is registered. This should be done during the change planning phase, not after the change is designed.
| Change element | US (FDA) | EU (EMA) | China (NMPA) | Brazil (ANVISA) | etc. |
|---|---|---|---|---|---|
| Classification | PAS | Type II | Supplementary | Category III | |
| Data package | Full comparability + validation | Variation dossier per EU template | Local format + Chinese translation | Dossier per RDC resolution | |
| Timeline | 4–10 months | 60–90 days | 60–200 days | 120–180 days | |
| Inspection risk | PAI possible | Rapporteur may request | NMPA inspection likely | ANVISA inspection possible |
2. Identify the critical-path market
The market with the longest regulatory timeline is the critical-path market. If China requires 200 days for a supplementary application and the US requires 4–6 months, the global implementation timeline is driven by China (assuming all filings are submitted simultaneously). Staggering submissions is an option but creates supply-chain complexity.
3. Leverage ICH Q12 where adopted
In markets that have adopted Q12 (US, EU, and increasingly Japan and Canada), propose established conditions and reporting categories in the original marketing application. A well-justified PLCM document can reduce the reporting category for future changes. Amgen and Pfizer have published case studies showing reduced reporting categories through the FDA EC pilot program.
4. Design the global data package
Design the comparability and validation studies to satisfy the most stringent market's requirements. This avoids the need to repeat studies for individual markets. Key elements:
Process validation (full-scale)
Analytical comparability (side-by-side testing)
Stability data (accelerated and long-term)
Risk assessment (aligned with ICH Q9)
Change control documentation from the PQS
5. Track the eCTD Module 3 lifecycle
After multiple post-approval supplements, Module 3 of the eCTD can diverge across markets. The same section (e.g., 3.2.S.2.2 for drug substance manufacturing process) may have been updated in the US but not yet in the EU or China, because the supplements are on different timelines. Maintain a Module 3 reconciliation tracker that records the current version of each section in each market.
Sources
ICH, Q12 Guideline: Technical and Regulatory Considerations for Pharmaceutical Product Lifecycle Management, Step 4, November 2019. https://database.ich.org/sites/default/files/Q12_Guideline_Step4_2019_1119.pdf.
FDA, Guidance for Industry: Established Conditions: Reportable CMC Changes for Approved Drug and Biologic Products. https://www.fda.gov/media/148476/download.
FDA, ICH Q12: What Industry Needs to Know. https://www.fda.gov/media/174238/download.
FDA, Certain Biological Products; Guidance for Industry. https://www.fda.gov/media/109615/download.
EMA, ICH Q12 Technical and Regulatory Considerations. https://www.ema.europa.eu/en/ich-q12-technical-regulatory-considerations-pharmaceutical-product-lifecycle-management-scientific-guideline.
EMA, Case Studies on Established Conditions (presentation). https://www.ema.europa.eu/en/documents/presentation/presentation-case-studies-established-conditions_en.pdf.
IFPMA/Clarivate, "Global Regulatory Approaches to Post-Approval Changes in Biotherapeutic Products: A Comparative Analysis Against WHO Guidelines," October 2025. https://www.ifpma.org/wp-content/uploads/2024/12/1025_Global-regulatory-approaches-to-post-approval-changes-in-biotherapeutic-products_Clarivate_IFPMA.pdf.
EFPIA, Response to Consultation on Variation Regulation. https://www.efpia.eu/media/whxay2h4/attachment_efpia-ve-response-to-consultation-on-variation_sept-2023.pdf.
Parexel, "Optimize your post-approval CMC change management in China with the ICH Q12 tool," April 2026. https://www.parexel.com/insights/blog/optimize-your-post-approval-cmc-change-management-in-china-with-the-ich-q12-tool.
Enkrisi, "FDA 2026 CMC Guidance: What Sponsors Must Do Differently." https://enkrisi.com/2026/01/07/https-www-enkrisi-com-insights-fda-2026-cmc-guidance-regulatory-strategy.
ECA Academy, "FDA adopts ICH Q12." https://www.gmp-compliance.org/gmp-news/fda-adopts-ich-q12.
ISPE Pharmaceutical Engineering, "A Vision for ICH Q12: Current Experience, Future Perspectives," September–October 2021. https://ispe.org/pharmaceutical-engineering/september-october-2021/vision-ich-q12-current-experience-future.
SG Systems, "EMA Variation Categories – Type IA, IB and II Quality & CMC Changes." https://sgsystemsglobal.com/glossary/ema-variation-categories-type-ia-ib-ii.
NoDeviation, "Post-approval of CMC changes under FDA, EMA and HSA guidance." https://nodeviation.com/post-approval-of-cmc-changes-under-fda-ema-and-hsa-guidance.
IntuitionLabs, "Biologics Comparability: A Guide to ICH Q5E & CMC Changes." https://intuitionlabs.ai/articles/biologics-comparability-guide.
21 CFR 601.12 — Changes to an approved application (biologics).
EU Regulation (EC) No 1234/2008, as amended by Commission Delegated Regulation (EU) 2024/1701.



